 dr.vision
∞ to screen
from distance to screen without glasses, continuous rather than in steps.
Start here
What suits you?
Find out in 2 minutes which procedure suits your eyes.
Start the Suitability CheckOr by age:
< 45yearsGet rid of glasses & contact lenses 45–64yearsGet rid of reading glasses 65+yearsCataract & glasses-free★★★★★ 5.0 · 376 Google reviews · 20,000+ procedures
Decide well
What you should know beforehand.
Who operates?Prof. Dr. Mehdi ShajariFOCUS Top Doctor · operates on every patient personally What does it cost?Laser from €3,498 · Lenses from €6,886Prices for both eyes Is it safe?Safety & risks When will I be fit again?Work, sports, driving Would you rather read in peace first?Decision Guide Freedom from GlassesProcedures
Laser or lens?
Laser eye surgery
SMILE ProSmartSightFemto-LASIKTrans-PRKPRKPresbyond (laser away your reading glasses)All laser procedures at a glanceLaser procedures compared ›Lens surgery
ICLLens exchange (reading glasses)Cataract surgery with premium lensLens types: trifocal, EDOF, toricLens types compared ›Start here
Something wrong with your eyes?
A thorough eye check-up with us clarifies what is behind it.
Book an eye check-up★★★★★ 5.0 · 376 Google reviews
Premium lens · Extended depth of focus
Sharp from the street to the screen.
Sharp from the street to the screen, usually without glasses: An EDOF lens extends the range of focus and usually causes fewer halos than a trifocal lens. Prof. Dr. Mehdi Shajari operates on you personally, with experience from over 20,000 procedures.
 12× FOCUSTop Doctor
A long range of sharp vision. Few side effects.
∞ to screen
from distance to screen without glasses, continuous rather than in steps.
depending on design: non-diffractive rarely, diffractive similar to trifocal
bothersome halos, depending on the design of the EDOF lens.
+1 D
usually only a light pair of reading glasses for fine print. Phone often without.
short
Usually days to a few weeks, because the brain hardly has to suppress a second image.
7.242 €
Guide price for both eyes with a cataract, under the GOÄ. Or in monthly installments, with a down payment from €3.90 a day*.
376 reviews. Average 5.0.
“The surgery itself was also absolutely uncomplicated for me: it felt like it was over after a few breaths – quick, professional and completely painless. […] Clear night vision took a few days longer, but here too the result is great. […] I see just as well as before with glasses, only without glasses.”
“My experience with the lens exchange was simply wonderful and highly professional from start to finish. […] He and his team are simply great; they take time, explain everything clearly and look after you exemplarily until after the surgery. […] Finally no more glasses.”
“From the first conversation with Prof. Shajari, I had great confidence in the upcoming surgery. The surgery process, the steps afterward, as well as the follow-up examination etc., confirmed my confidence!”
“Dr. Shajari knows what he is doing and works very professionally. I always felt well advised and the surgery went quickly and without problems.”
Four patients. In their own words.
I wanted my life back – without glasses, without headaches.
Now I can already read things again.
I was allowed to take off the bandage that very afternoon.
I saw wonderfully bright light.
The EDOF lens in five answers.
For anyone with three minutes. Each answer leads to the detailed chapter.
EDOF stands for “Extended Depth of Focus”. The artificial lens does not form a single focal point, but a stretched range of sharp vision from distance to about arm's length.
To the chapterEDOF if you often drive at night, work a lot at a screen and accept a light pair of reading glasses. Trifocal if you mainly want to live without reading glasses and accept halos.
Daily-life checkPhone and large print often work without; package inserts and fine print usually with a light pair of reading glasses. With mini-monovision, the near range becomes larger.
Reading with EDOFGenerally clearly calmer than with trifocal lenses. Slight rings around lights are possible; they are rarely bothersome. Contrast is close to a monofocal lens.
Night simulationAt dr.vision, €7,242 for both eyes with a cataract, billed privately under the German fee schedule for physicians (GOÄ), including pre-operative examination, surgery, lenses and aftercare. €244 more than with a monofocal lens, €634 less than with a trifocal lens.
CostsStretch the focus instead of splitting it.
An EDOF lens is an artificial lens that stretches a single point of sharpness lengthwise: from the street across the dashboard to the laptop. A trifocal lens, by contrast, jumps between three points of sharpness. Less splitting, fewer halos.
Steps
Similar to trifocal lenses, but with a few, flat steps. A little more near vision, occasionally slight rings around lights.
Wave
A finely modeled zone in the center of the lens extends the focus without diffraction rings. Light effects almost like with a monofocal lens, but a little less near vision.
Far/near
The dominant eye sees at distance, the other is set slightly nearsighted. Together, the range of sharp vision reaches further into near vision.
Anyone who takes photos knows depth of field: with a small aperture, everything from the foreground to the horizon is sharp; with a wide-open aperture, only one plane. A monofocal lens behaves like a wide-open aperture: it is set for one distance, and in front of and behind it things quickly become blurry. An EDOF lens lengthens the sharp zone; non-diffractive models do not split the light into separate images in the process, diffractive ones only to a small degree. That is why there is no “jumping” between distance and screen, and the brain does not have to suppress a second, blurry image.
The limit lies in near vision: the further the focus is stretched, the more contrast it costs. EDOF lenses are therefore deliberately built to be very good up to about arm's length and to need slight support when reading small print.
The term EDOF covers lenses with very different optics. Diffractive EDOF lenses reach somewhat further into near vision but can show slight rings around lights. Non-diffractive EDOF lenses have night vision almost like a standard lens, but their range ends sooner. Between EDOF and monofocal lie the “monofocal plus” lenses, which improve the intermediate range only slightly. Which design you receive depends on your wishes, your daily life and your measurements. The page Lens types gives an overview of all types.
With a cataract, the clouded lens has to be replaced anyway; the EDOF lens is then one way to get rid of both distance glasses and computer glasses at the same time. With refractive lens exchange from about age 45, it replaces your own, still clear lens that can no longer focus. Under 45, laser eye surgery or an ICL is usually the better choice.
Your daily life decides. Not the lens.
The EDOF lens suits people who drive a lot, also at night, and work a lot at a screen; the trifocal lens suits people who mainly want to live without reading glasses. Both reach the same visual acuity at distance.
Tap what shapes your daily life. Multiple selection possible.
Your orientation
Tap what applies to you.
The result adapts with every answer.
Orientation, not a diagnosis. Which lens is medically suitable is only shown by the pre-operative examination with biometry, macular OCT and corneal measurement.
Six daily lives, six answers.
80 km every day, in winter there and back in the dark. Almost everything speaks for EDOF here: calm night vision, a sharp dashboard and navigation display.
Eight hours at the laptop, two monitors, television in the evening. The intermediate range is his daily life; EDOF covers it without glasses.
Ball, fairway and green are distance to intermediate range. The scorecard usually works in daylight without glasses too.
Two books a week, crossword puzzles, hardly any night driving. Here the trifocal lens is often the better choice, or EDOF with mini-monovision.
Fine work at 30 cm, for hours. Trifocal reaches further into near vision; with EDOF, a pair of work glasses would remain.
At night on the highway, contrast counts. Here we advise non-diffractive EDOF or monofocal, not trifocal.
Example daily lives, not real patients.
Two of three distances without glasses.
With an EDOF lens, distance and screen are sharp; for small print at reading distance, a light pair of reading glasses usually helps. Tap a lens type and compare with trifocal and monofocal.
Tap a lens type. The three images show what you see with it without glasses.


Driving, cooking, laptop, dashboard without glasses, with almost monofocal contrast and usually fewer halos than trifocal. A phone with large print often works without in good light, a package insert with light reading glasses.
Reading without glasses too, but with more halos in the first months and slightly less contrast at dusk. More on the page Trifocal lens.
The standard, with the best contrast and the fewest light effects. More under Lens types.
Astigmatism? Every EDOF lens is also available as a toric lens. Without correction, astigmatism noticeably shortens the range of sharp vision. More about the toric lens.
The most important difference to the trifocal lens.
Halos and rays around headlights are usually less frequent with EDOF lenses than with trifocal lenses; with non-diffractive EDOF lenses, almost as rare as with a standard lens. Choose an effect to see what it is about.

Simplified depiction. Photo: Patrick Tomasso, Unsplash (CC0).
Tap an effect. The photo shows what it looks like.
The more a lens distributes the light, the less contrast remains for each image. EDOF lenses distribute less than trifocal lenses; their contrast is therefore close to a monofocal lens. In studies, EDOF lenses on average perform somewhat better than trifocal lenses for contrast vision and glare, and worse for near vision. For people with slight retinal changes, this is an important reason for EDOF.
Because the EDOF lens does not create a second, blurry image that has to be suppressed, getting used to it is shorter than with trifocal lenses. Distance is usually clear the day after surgery, the intermediate range within the first days. With mini-monovision, the brain needs one to two weeks to bring the two eyes together.

EDOF or trifocal?
We will find out together. Call us.
Jana from our Patient Care team answers your questions and arranges the pre-operative examination with Prof. Dr. Mehdi Shajari. Phone available 24 hours, WhatsApp Mon–Fri 8:00–19:00, Sat 9:00–15:00.
Often none for the phone. A light pair for the package insert.
With an EDOF lens, most people read large print and their phone in good light without glasses. For small print, a light pair of reading glasses of about +1.0 D is usually enough, clearly weaker than before. With mini-monovision, the near range becomes larger. This is what it looks like in daily life:
| Task | EDOF in both eyes | EDOF with mini-monovision | Trifocal |
|---|---|---|---|
| Driving, road signs | without glasses | without glasses | without glasses |
| Navigation display, dashboard | without glasses | without glasses | without glasses |
| Laptop, monitor | without glasses | without glasses | without glasses |
| Phone, large print | usually without, good light | without glasses | without glasses |
| Newspaper, book | often light reading glasses | usually without | without glasses |
| Package insert, price tag | light reading glasses | often light reading glasses | usually without, good light |
| Sewing, fine work | Reading glasses | light reading glasses | usually without |
Typical experience values, individually different.
With mini-monovision, we set the dominant eye for distance and the other slightly nearsighted, by about −0.5 to −0.75 D. Together with the extended depth of focus of the EDOF lens, the range of sharp vision of both eyes then reaches further into near vision. The difference between the eyes is so small that most people do not notice it; distance stays sharp with both eyes. Whether you tolerate monovision, we test beforehand, with a contact lens if needed.
With classic monovision using monofocal lenses, the near eye is set clearly more nearsighted (−1.0 to −1.5 D). This brings more near vision but costs some depth perception. Mini-monovision with EDOF lenses uses only a small difference, because the lens itself already has a long range of sharp vision. Depth perception is practically preserved.
Because distance and intermediate range usually work without glasses, most people no longer need progressive glasses. For fine print, a simple pair of reading glasses is enough, often from a drugstore, usually around +1.0 D. Many keep them in only two places: at the desk and next to the bed.
The EDOF lens in direct comparison.
EDOF lies between the two classics: more freedom from glasses than the monofocal lens, calmer night vision than the trifocal lens. Monofocal plus is an improved standard lens with a little more intermediate range. In detail, with the study evidence: Lens types compared.
On the left always the EDOF lens, on the right the chosen alternative.
| Criterion | EDOF | Trifocal | Monofocal plus | Monofocal |
|---|---|---|---|---|
| Principle | Stretched range of sharp vision | Light split between three focal points | Monofocal with slightly extended focus | One focal point |
| Distance | sharp | sharp | sharp | sharp |
| Screen 60–80 cm | sharp | sharp | partly without glasses | Glasses |
| Reading 40 cm | light reading glasses for fine print | mostly without glasses | Reading glasses | Reading glasses |
| Halos at night | diffractive similar to trifocal;non-diffractive hardly any | bothersome in 3 of 10 at first, under 1 of 10 after 3 months | rare | rare |
| Contrast | almost like monofocal | somewhat lower | like monofocal | best |
| Adjustment | Days to a few weeks | Weeks to about 3 months | hardly | hardly |
| After previous laser eye surgery | often well suited | in individual cases | yes | yes |
| With macular or retinal disease | in individual cases | no | yes | yes |
| With astigmatism | yes, toric | yes, toric | yes, toric | yes, toric |
| Guide price both eyes (cataract) | €7,242 | €7,876 | €7,242 | €6,998 |
Four steps. Choosing the lens is the most important.
The surgery takes about 20 minutes per eye and is the same for every lens. With EDOF lenses, we also decide during the pre-operative examination whether mini-monovision makes sense for you. The second eye usually follows one week later.
Step 1 of 4

Understanding your daily life.
Bring: glasses, glasses prescription, previous findings, medication list.
Schedule an initial consultationStep 2 of 4

Measuring and setting the target power.
You go home with a written lens recommendation and a cost estimate.
What is mini-monovision?Step 3 of 4
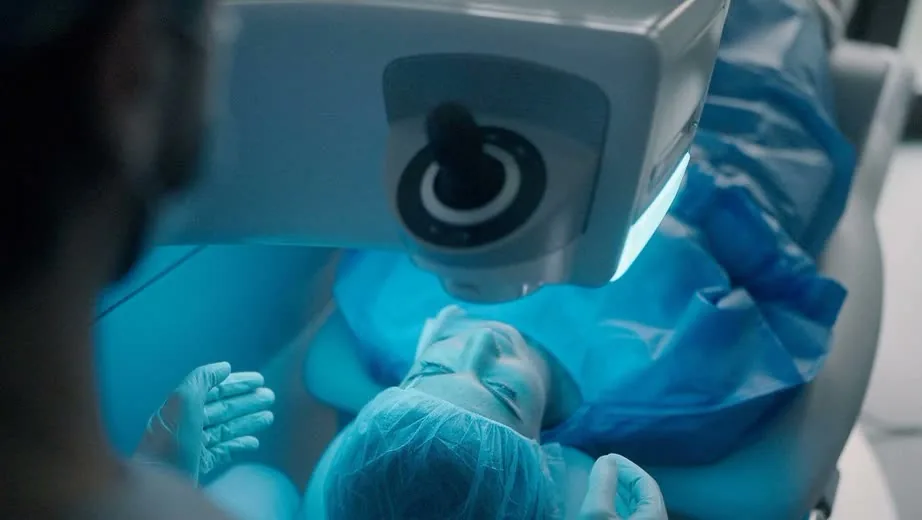
About 20 minutes per eye. Awake, numbed with drops.
Please come accompanied; you will not drive yourself on this day. The page Cataract surgery shows the surgical procedure in detail.
Step 4 of 4

Follow-up checks until everything settles.
Drops for about four weeks. The follow-up checks are included in the price, emergency number around the clock.
Surgery on both eyes on one day is possible and safe. With EDOF lenses, especially with mini-monovision, we recommend a one-week gap: the result of the first eye shows where the target power landed, and you notice for yourself whether the near range is enough for you. After that, we set the second eye.
| Activity | From when | Note |
|---|---|---|
| Screen, television | immediately | Take breaks, your eyes tire more quickly at first |
| Work (office) | Day 2–3 | Dust, construction site, kitchen: one week |
| Driving | usually 1 week after both eyes have been operated on | In some cases already after the first eye; the doctor decides at the follow-up check |
| Sports, swimming, sauna | light exercise after about a week, swimming and sauna after 14 days | No rubbing, no water in the eye |
Fewer side effects than trifocal. The same surgical risks.
The optics of the EDOF lens generally cause halos less often than a trifocal lens; the risks of the surgery itself are the same for all lenses. The safety rate for procedures performed by Prof. Dr. Mehdi Shajari is 99.9%. The most common later consequence is secondary cataract.
Slight rings around lights, especially with diffractive EDOF lenses. Not a surgical error, but a property of the optics.
depending on design: non-diffractive rarely bothersome, diffractive similar to trifocal
different depending on design: with non-diffractive EDOF lenses they are rare, with diffractive ones about as common as with trifocal lenses.
Choose the design according to your night-driving profile, measure the pupil, show the effects beforehand.
For small print, the range of sharp vision of the EDOF lens is often not quite enough. This is not a complication, but the known limit of this lens.
in many people
for fine print, less often in good light.
Discuss clearly beforehand, offer mini-monovision, light reading glasses. If you do not want that, you are better advised with trifocal.
The power achieved differs from the target. EDOF lenses forgive small deviations somewhat better than trifocal lenses.
about 2 out of 10
are slightly off, an enhancement is needed in about 5 of 100.
Two formulas, a one-week gap between the eyes; if a residual error is bothersome within 6 months, we discuss a laser fine adjustment case by case.
The capsule behind the artificial lens clouds months to years after surgery, and vision becomes milky again.
about 1 in 10
within five years.
YAG laser within a few minutes, outpatient, generally painless. After that, it generally does not come back. More under Secondary cataract.
Fluid in the center of the retina a few weeks after surgery, vision becomes blurrier.
about 1 in 100
more common with diabetes.
Anti-inflammatory drops, OCT if suspected. Usually heals with drops.
Flashes, a shower of dark spots, a shadow in the visual field. Possible weeks to years after surgery.
about 1 in 100 or less in the first years (large studies from France and Australia)
more common with high nearsightedness.
Examine the retina beforehand, explain warning signs, emergency number.
Bacteria inside the eye. Signs in the first days: increasing pain, red eye, worse vision.
under 1 in 1,000
Antibiotic into the eye at the end of every surgery, sterile operating room, follow-up check the day after the procedure, emergency number around the clock.
Frequencies from our own analysis (n = 1,100, 2022–2026) and literature.

Because the best lens is the one that fits your day.
One surgeon for both eyes, over 20,000 procedures, 5.0 stars from 376 reviews. And a consultation that begins with your daily life, not with the lens catalog.
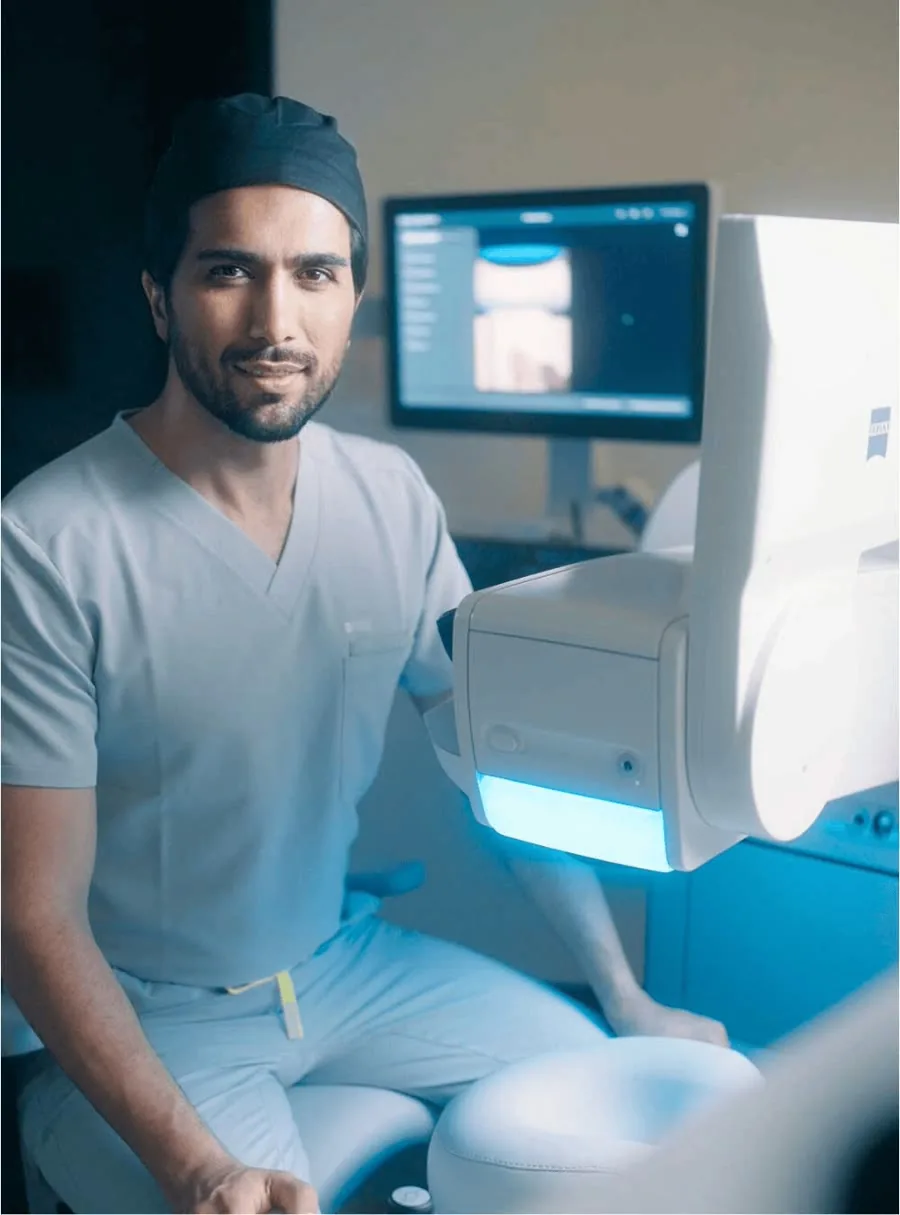
Every procedure: Prof. Dr. Mehdi Shajari. Personally.
He plans the lens and target power with you, including mini-monovision. Specialist in ophthalmology and professor (German title: außerplanmäßiger Professor) of ophthalmology, over 80 publications on lens and corneal surgery. On @fragdrvision he explains to around 120,000 people how eyes work. At dr.vision, he operates not with a changing team, but himself.
“Cataract surgery is technically routine. What is not routine: finding out which lens suits your life. And saying honestly when the simplest one is the best.”
Prof. Dr. Mehdi Shajari
Prof. Dr. Mehdi Shajari has published numerous papers on freedom from glasses, teaches, and has trained several colleagues in this field.
What you get with us.
One surgeon
Both eyes, every procedure. Over 20,000 procedures in his career.
Reviews
5,0
376 Google reviews
Lens choice
Even if the simplest is the best.
Lens, retina, macular OCT, eye pressure, biometry with two formulas. You go home with a written recommendation and a cost estimate.
5,0
★★★★★
from 376 Google reviews
No changing team. Whoever does your pre-operative examination also operates on you.
24/7
Emergency number around the clock. All follow-up checks included.
If an enhancement is medically sensible, under our concept it is usually possible within 6 months without a co-payment.
Optical biometry and two independent formulas. With premium lenses we adjust the calculation for the second eye.
Monofocal, EDOF, trifocal and toric. We recommend what suits your daily life, even if it is the simplest lens.
Billing according to GOÄ, your written cost estimate after the pre-operative examination, on request financed with a down payment from €3.90 a day.
Jana answers questions about lenses, appointments, and costs via WhatsApp, usually within 10–15 minutes, Mon–Fri 8:00–19:00, Sat 9:00–15:00. We are also available by phone around the clock.
Patient Care
Junghofstraße 16, free parking in the building.
A look inside the practice and the team.






Transparent prices. In writing before surgery.
€7,242 for both eyes with an EDOF lens for a cataract, as a guide price including pre-operative examination, surgery, lenses and aftercare. That is €244 more than with a monofocal lens (€6,998) and €634 less than with a trifocal lens (€7,876). Billing follows the German fee schedule for physicians (GOÄ), and you receive the written cost estimate after the pre-operative examination. For refractive lens exchange, the same guide price of €7,242 applies.
€7,242Guide price · both eyes, cataract · billed under GOÄ
* Representative example: €6,497.47 net loan amount (€7,242 with EDOF lens, €744.53 down payment) · 72 months · fixed borrowing rate 9.49% p.a. · 9.90% effective annual interest rate · monthly installment €118.72 · total amount €8,547.84 (with down payment €9,292.37) · via medipay. Alternatively 0% over 12 months directly at dr.vision.
For a cataract, private health insurance plans often reimburse a large part of the surgery, depending on the plan; a share of the cost remains with you. Many plans treat the EDOF lens as an additional service: the monofocal portion is often reimbursed and you pay the extra charge yourself; some plans cover more. For lens exchange without a cataract, reimbursement depends on the plan and has to be checked case by case. More under Private health insurance.
For a cataract, surgery and a standard lens are eligible for Beihilfe (allowance for German civil servants) under the GOÄ; for the extra charge for the EDOF lens, each federal state has its own rules. For lens exchange without a cataract, Beihilfe generally does not reimburse. More on the page Beihilfe.
dr.vision is a private practice without a statutory insurance license. The statutory health insurer does not reimburse our treatment; you pay yourself, after a written cost estimate and, on request, financed with a down payment from €3.90 a day. You can declare the costs as extraordinary expenses in your tax return. Whether and how much the tax office recognizes depends, among other things, on your reasonable burden. More under Statutory health insurance.
At dr.vision, the difference to the monofocal lens is €244 for both eyes. In return, distance glasses and computer glasses are mostly no longer needed; a simple pair of reading glasses for fine print often remains. If you currently wear progressive or office glasses, you know what they cost. In detail: What does lens surgery cost? and Financing.
Medical costs you pay yourself may be deductible as extraordinary expenses (§ 33 EStG) to the extent that they exceed the reasonable burden. For a cataract, medical necessity is given; for lens exchange, it is assessed case by case. Details on the page Tax; we are not tax advisors.
You are not alone
Questions about reimbursement? Our Patient Care team can help: 069 509 586 770 (available 24 hours)
| What | Artificial lens with extended depth of focus (Extended Depth of Focus) |
|---|---|
| Without glasses | Distance and intermediate range up to about arm's length; fine print usually with light reading glasses |
| Night vision | bothersome halos depending on design: non-diffractive rarely, diffractive similar to trifocal |
| Designs | diffractive, non-diffractive, with mini-monovision on request |
| Well suited for | Night drivers, screen work, sports, after previous laser eye surgery |
| Astigmatism | toric EDOF lens, extra charge on request |
| Costs for both eyes | €7,242 for a cataract and for lens exchange |
| Insurance | Private health insurance and Beihilfe (allowance for German civil servants) under the German fee schedule for physicians (GOÄ), extra charge depends on the plan · patients with statutory health insurance pay themselves |
| Surgeon | Prof. Dr. Mehdi Shajari |
| Location | Junghofstraße 16, 60311 Frankfurt am Main · Düsseldorf and Stuttgart 2027 (preliminary talk already in Frankfurt) |
Go deeper.
This page explains the EDOF lens. The neighboring topics in detail:
All distances without glasses, with halos in the first months. Experiences and exclusion criteria.
To the trifocal lens ComparisonStudy evidence, freedom from glasses, halos and contrast in a big comparison.
View comparison OverviewMonofocal, monofocal plus, full-range, EDOF, trifocal and toric at a glance.
To the overview AstigmatismHow the axis is aligned and what happens if the lens rotates.
Learn more Without a cataractGet rid of reading and distance glasses before the lens becomes cloudy.
To lens exchange With a cataractProcess, surgery days and prices at dr.vision.
To the surgery pageStill have questions?
Answers from the consultation hours of Prof. Dr. Mehdi Shajari and his team.
Neither is better in principle. The EDOF lens offers calmer night vision and more contrast, the trifocal lens more freedom from glasses when reading. If you often drive at night and work a lot at a screen, you are usually happier with EDOF; if you read a lot and want to avoid reading glasses, with trifocal.
For people with a cataract or lens exchange from about 45 who want to see distance and screen without glasses, drive a lot, also at night, and accept a light pair of reading glasses for fine print. After previous laser eye surgery, too, EDOF is often a good choice; the lens calculation is then more complex, but with new calculation models it has become clearly more accurate.
Caution is needed with retinal or optic nerve disease. We do not use a trifocal lens then. A non-diffractive EDOF lens may be possible depending on the findings; often a monofocal lens is the safer choice. The macular OCT in the pre-operative examination decides this.
Yes, as a toric EDOF lens. Without correction, the astigmatism would noticeably shorten the range of sharp vision. The toric extra charge is quoted individually after the measurement.
Not for distance and screen. Large print and the phone often work without glasses in good light; for fine print such as package inserts, a light pair of reading glasses of about +1.0 D is usually enough. With mini-monovision, the near range becomes larger.
Yes. Calm night vision is one of the main reasons for EDOF. Slight rings around lights are possible; they are rarely bothersome and usually less frequent than with trifocal lenses.
The dominant eye is set for distance, the other slightly nearsighted, by about −0.5 to −0.75 D. Together with the EDOF optics, the range of sharp vision then reaches further into near vision. Depth perception is practically preserved.
Usually only days to a few weeks, shorter than with trifocal lenses, because hardly any second image has to be suppressed. With mini-monovision, the brain needs one to two weeks.
Generally a lifetime. The artificial lens does not wear out and usually stays clear permanently. Years later, a secondary cataract can occur, which is treated with a short laser procedure.
With EDOF lenses, especially with mini-monovision, the second eye usually follows one week later. That way we can align the second eye with the result of the first.
The guide price for both eyes with an EDOF lens for a cataract is €7,242, including pre-operative examination, surgery by Prof. Dr. Mehdi Shajari, lenses and follow-up checks. With a monofocal lens it is €6,998, with a trifocal lens €7,876.
dr.vision is a private practice: Patients with statutory health insurance pay themselves, on request financed with a down payment from €3.90 a day. For cataracts, private health insurance and Beihilfe (allowance for German civil servants) reimburse the surgery proportionally according to GOÄ (a personal share generally remains), and the surcharge for the EDOF lens depending on the plan. For lens exchange without a cataract, reimbursement is assessed case by case.
Medically reviewed by Prof. Dr. Mehdi Shajari · As of October 2026
Not ready yet? Everything important to read again and to pass on.
Arrives by e-mail in about 60 seconds. No newsletter, just the guide and, if you wish, a follow-up from Patient Care. Privacy policy
How would you like to continue?
The first appointment is a free consultation about your daily life and which lens suits you. This is followed by the detailed pre-operative examination with Prof. Dr. Mehdi Shajari: lens, retina, macular OCT and biometry. You go home with a written lens recommendation and a cost estimate.
In Frankfurt, Junghofstraße 16 · all measurements included
Our locations.
 Opening hours
Junghofstraße 16, 60311 Frankfurt am Main
 Opening 2027
Breite Straße 69, 40213 Düsseldorf (in the Neuer Stahlhof, corner of Graf-Adolf-Platz)
Until opening: preliminary talk in Frankfurt, Patient Care plans your travel.
Plan route Opening 2027
Lautenschlagerstraße 23, 70173 Stuttgart (2nd floor, step-free access)
Until opening: preliminary talk in Frankfurt, Patient Care plans your travel.
Plan routeMy name is Simone Richter. Before the treatment I had the problem, above all or increasingly, that I could not see well at all anymore at near and intermediate distance, which bothered and limited me extremely. For one thing at work, but of course also in private life, when you go hiking and want to read a map and can't see anything anymore and your glasses fog up or you lose them or break them, which I'm a great artist at. That bothered me a lot, limited me a lot. On top of that, wearing glasses felt to me like it triggered migraines, so the headaches bothered me a lot too, and that is why I decided on the surgery.
I got a lens exchange, so a new trifocal lens, which also comes with certain compromises, I have learned you always have to make a compromise, and and since the topic of freedom from glasses was very important to me, I decided on the trifocal lens.
So I actually came across Professor Shajari on the internet and had the first appointment with the intention of slowly getting used to the idea of progressive glasses. That would have been the next step. I had not dealt with the topic of surgery at all beforehand, because basically I am rather against having anything operated on without great need. And then in the conversation I felt, how should I put it, well taken care of. I did not feel pushed in any direction at all, just got information I did not have before. And with that I started to look into the topic. In between I also dropped it again, but then, through everyday activities, everything I just mentioned, hiking, swimming, cycling, where glasses really torment me, I thought, okay, I'll try this, and I also simply built up trust over time. That was all something that gave me a lot of reassurance, because Professor Shajari always took a lot of time. You know how it is with doctors, and I understand it too. There is a lot of pressure with queues of patients, and in the end you probably always have to answer the same questions. But I always had the feeling that there was enough calm to answer my questions.
The actual course of the surgery, from the pre-operative examinations to the appointment, goes very fast, it is very easy, much easier. I panicked a lot the evening before the first eye and thought, oh my God, how will this go? My head will be screwed down Hannibal Lecter style so that I don't flinch. And I worked myself into my horror scenarios. And it was all actually very relaxed. A very, very nice, good-humored team in the surgery center as well, which I think also helps a lot as a patient. And yes, it goes in no time, you don't feel anything, I think I can say that, and you go home again and everything is fine.
What was very astonishing for me was that I actually did not feel it at all, so during the surgery 0.0 pain. There was one point where Professor Shajari said, now comes a little pressure, and a little pressure came. To call that pain would be saying too much, but you really don't feel more than that. I must say, though, that between the two surgeries, from the first to the second eye, I felt even more unsure, even though that was always well handled and explained.
I think before the surgery it was also very important that, in my perception, it was explained realistically. It was explained well that it is a compromise, that in some ranges of vision it would get worse, but that in sum a visual ability that allows freedom from glasses will result. Now of course that is very subjective. So what does it mean, I will see worse in some ranges? That was a really big panic point for me and it stayed very strong in the time from the first eye to the second eye, because after the first eye I of course had the issue that I had one eye not operated on that doesn't see well and one operated eye that sees so-so after the surgery. Already much better. I also got a smile from people often, because on the second day I could already read with the operated eye, which would have been unthinkable before the surgery and which was also a really big pain point for me. But this panic still led me to this fear, what have you done, you had something operated on for the worse, because of course with glasses an operated and a non-operated eye create a really awkward situation. And now, today, day one after the surgery on the second eye, I am actually very happy at the moment.
I did good research beforehand. I also called my health insurer to ask how they view such operations. I deliberately chose Professor Shajari because he also has a good reputation. You hopefully only do this once in your life, and you don't have, you don't know, so I asked around my circle of acquaintances. What experiences have people had with these operations, which interestingly didn't give such positive feedback in my case. However, they were not patients of Professor Shajari, and some of it was also a while ago, I have to say. Medicine has surely progressed since then. That unsettled me and it was also one of the reasons why I first backed away from the operation again in my carousel of thoughts. But I believe in tapping all the information channels you have, asking all your questions, and really choosing a doctor who gives you a good gut feeling. Because I believe, with all these topics, you can check a lot of facts, and you should. But you also have to have a good feeling.
And I am not now, it was partly also an indication with the cataract in my case. And I am not that old, I could have gotten around this surgery with glasses for a while longer. I am 55, I could certainly have worked around such a surgery with glasses for a while. You have to really think it over carefully, I believe, then that also gives you a good feeling yourself. And if you then feel in good hands, which was the case here, then it can work well.
My name is Björn Kannegießer. For many years I wore glasses, which was especially a problem when reading, when you used your phone, and so on, checked e-mails. It no longer worked without glasses and at some point it reached a degree where you say, if there were a change, what would you do? And to get rid of the glasses, because they are always an obstacle somewhere, every day up, down, up, down, where are the glasses, forgotten again, and so on. And so we said, what alternatives are there, and then we looked into it and we have now taken the step, so to speak.
Yes, my wife is very savvy on the internet; whenever we have to buy, need or compare things, also price comparisons, my wife is always very good at that, she always has a good knack for it, and she took on the matter and came across this, so to speak, and then we tackled it here. Yes, of course you have a lot to do with social media, so also with computers, and it was always annoying, and what I also noticed was that I couldn't wear sunglasses anymore, because either you have sunglasses on and then you can't see anything, I couldn't read either at that moment, so I had to take them off, put the normal glasses on, and it was always up and down like that, sometimes you had two pairs of glasses somehow, the sunglasses you took along and the normal ones. I do have progressive glasses that also tint, but it wasn't the same as sunglasses, and at some point it was all too much for me, and this fiddling with contact lenses, in, out, lost, where is that thing, it was all way too much effort for me somehow and not an alternative for me, and to get rid of these glasses, we actually thought, let's take the step if it's feasible. So even in the first two days I still reached for my glasses by reflex, because I usually always had them on my head, as that was the easiest, and after two, three days it gets less, and now I can already read things again, I have that as of today, the other eye was still bandaged and so on. Now I first have to focus a bit, but I can read things again that I used to, because that's how it is, you know, so it's definitely a good thing, so now of course I first have to acclimate the left one a little, so to speak, but you can already notice it, it's definitely an improvement.
So absolutely, I felt absolutely comfortable here with the professor, the empathy is there, I felt well taken care of, also in the conversations, and of course during the procedures and so on, so I never felt uncomfortable in any way, and from that side I can recommend it, I would do it again, but I am annoyed that I did not do it earlier, I have to say quite honestly.
I am Margit Tappeiner, I am an architect and I am 60 years old.
So I have worn glasses since I was in my mid-20s, and I am farsighted, nearsighted, astigmatic and I also have a squint. So I was used to getting along with my glasses, which I got newly fitted every two years. But what I did notice was, when I criticized samples, these dull colors again and again and this yellow cast. I also missed the brilliance of my work. I mean, I always thought the colors would be more brilliant, the shapes sharper, the way I plan and build. And it was a creeping process, and that is why I did not think it was so important.
I hadn't expected it to reach me now, also because I'm apparently quite young for a cataract. And it is probably actually hereditary. My mother also had a cataract at a very early age.
My husband is a patient of his, my husband is a doctor too. And they hit it off right away as well. And yes, when I get a recommendation from a very good doctor, there is something to it.
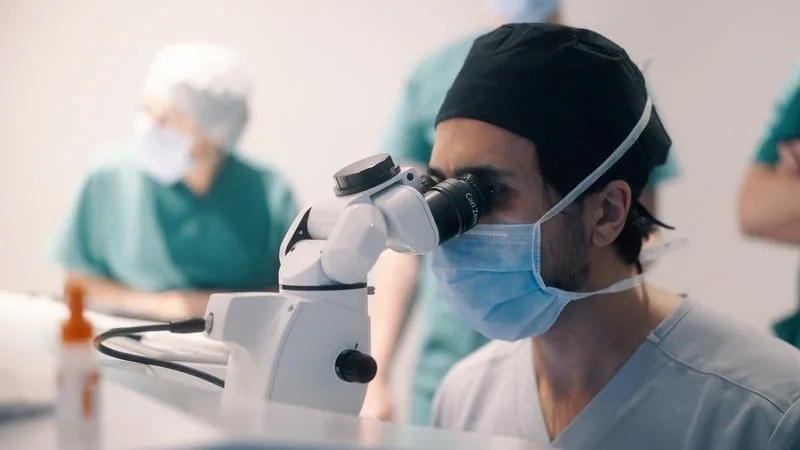
Impressive equipment, everything brand new, everything as far as I can judge of the highest quality, and then also the explanation by Shajari himself on the big screens. That way it is simply shown to you visually what is going on in your eyes and not just explained.
At 60 you have so much behind you that you don't get anxious now. And Shajari took away every fear, I have to say. I knew it was a standard procedure, and that is how it was.
So yes, on the same day, I was operated on in the morning, and the most unusual thing was that it is done in two stages. First one eye, then the other. And in this case with a gap of one week. So one eye was operated on and seeing correctly and the other was still with a refractive error. And that was very odd, because I don't wear lenses, because of the squint no lenses. So I could not compensate with a lens on the not yet operated eye. So I had glasses where I took one lens out. So that was pretty spooky for a week.
But yes, I was allowed to take off the dressing already in the afternoon. And then put it on again at night for sleeping. That was great, that was fantastic, but of course everything was glaring. Sensitive to light, but it was wonderful. It was like a new view of things.
Yes of course, I have. Yes, the whole community has already turned up at his place.
My name is Eva Maria Hohmann. On July 16, I had my second eye surgery with Professor Shajari. I received the second lens implant. The first surgery was on July 9, and I am very, very happy with the results. I also found the surgery, which took place while I was awake, so without anesthesia or sedatives, still quite bearable, because I could take part by looking into the light. And Professor Shajari exchanged the lens in the process. After each surgery, I drove home and felt well.
I was simply told by my treating eye doctor that I have a very strong cataract in one eye, and in the other eye as well. And on top of that I am also strongly farsighted. Different on both sides. The right eye was more affected, the left somewhat less. And Professor Shajari operated on the right eye first.
Yes, when I looked through the dressing the next morning, I first noticed that I saw wonderfully bright light. And then there was a note on the kitchen table and I thought, I just read something there. That was no longer possible at all with this eye. So I really could not read anything without glasses.
But I kept having moments of tiredness where I felt exhausted and really just thought, I have to get up now. I just have to go somewhere else now and stop looking at the screen. And in the evening after work I also noticed it very strongly, the problem with the refractive error. So in the evening after work I was no longer able to sit down in front of the TV. It was simply too much for me. And that gradually became more intense over the last months.
Then, thank God, came the preventive check-up at my eye doctor. And then it also came out that the cataract there was already so advanced. And the really very kindly meant advice not to get new glasses but really to think about a lens exchange.
Through my treating eye doctor. The two apparently know each other. He recommended Professor Shajari to me, but also knew patients who had already been to him. And they were all very satisfied. And I also watched one or two YouTube videos by Professor Shajari. And that actually gave me trust as well. I think it is very important, when someone operates on my eyes, that I trust that person.
No, I had no pain. Every now and then I felt a more or less strong pressure. But then Professor Shajari also said, now it presses. Well okay, then it presses. It is bearable and I did not concentrate on it. I just breathed deeply. It does not last long either, this moment where it presses, it comes and it goes. Then it is already fine. So it is not like it presses for half an hour. It passes very quickly. So Professor Shajari, I noticed, also has a very skilled hand at the eye, he also put on this dressing that opens the eye completely. I had only seen that in a picture on YouTube and thought, oh man, but you don't feel it at all. It really can't be noticed. I mean, the eye is numbed through and through beforehand. So the eyelids, the eyeball, they are really insensitive then.
Yes of course, I would always recommend him to anyone who has questions about their eyes, who maybe also has little time, can't find an eye doctor who has an appointment now. With specialist physicians there are often problems getting appointments. I can really only recommend him.
I also found the initial examination, when I was here for the very first time, very detailed and very appealing. Everything was examined with optical devices, very thoroughly. And so Professor Shajari had all my values before the surgery. And I had the feeling, yes, they know what they are doing here. And there are examination devices here that regular eye doctors do not have. For example, the measurement of the eyeball, they do not do that. The other device, the scanner camera for the retina, the back of the eye, I knew that one. The other measuring devices for the eyes, where the glasses prescription is measured, where visual acuity is measured, those are familiar too. But this is really thorough, and I also found the resident physicians and the assistants who performed the examinations all very friendly.
I would simply say, be honest with yourself. If you have an eye problem, tackle it, don't run away from it. It only gets worse with time. You could also have an accident or experience something unpleasant that does not have to be, if your eyes are in the best condition. And eye treatment is, as I once said, not the greatest party, but it goes very fast. As I said, in a nice environment, Professor Shajari is so friendly, also during the surgery, you simply forget what is actually being done. That is a good thing too, and just go, do it and then it is fine.